

Reconciling Autonomy and Paternalism in End-of-Life Medical Decision-Making: A Bioethical Analysis
 By Dr. Robertson Prime, Research Fellow
Updated October 24, 2026
19 min read
About 3,700 words
This dissertation introduction example addresses one of the oldest tensions in clinical ethics: how to weigh autonomy and paternalism when patients make end-of-life decisions. It is a complete Chapter 1 for a conceptual bioethical analysis rather than an empirical study.
Every reference in the chapter has been checked against its published source. Because the study is philosophical, it uses central propositions instead of hypotheses, and the breakdown near the end explains how that changes the chapter.
On this page
What this example shows
- A conceptual method: the study argues from principles and cases instead of collecting data.
- Propositions, not hypotheses: each research question has a claim the analysis will defend.
- Four case types: capacity, advance directives, futility disputes and medical aid in dying.
- A clear contribution: the chapter promises a framework that gives more determinate guidance than balancing alone.
Background of the Study: Autonomy and Paternalism at the End of Life
Introduction
End-of-life medical decision-making sits at the point of sharpest tension between two of bioethics’ most foundational commitments: respect for patient autonomy and the physician’s obligation to protect patient welfare, a tension that becomes especially acute when a patient’s capacity, values, or expressed wishes are ambiguous, contested, or apparently in conflict with their own long-term interests (Beauchamp & Childress, 2019).
While the principle of respect for autonomy has, over the past half-century, displaced overt medical paternalism as the dominant normative orientation in Western clinical ethics, end-of-life care continues to generate cases in which clinicians, families, and ethics committees must decide whether, and to what extent, some degree of paternalistic constraint on a patient’s stated wishes remains ethically defensible (Jonsen et al., 2022).
This chapter presents a bioethical analysis reconciling autonomy and paternalism in end-of-life decision-making, examining the philosophical foundations of each principle, the specific clinical contexts in which they come into tension, and the conceptual and practical resources available for their reconciliation, situating the analysis within the broader normative and clinical literature on end-of-life care ethics.
Background of the Study
The principle of respect for autonomy, formalized within biomedical ethics through the influential four-principles framework, holds that competent patients possess the right to make informed decisions regarding their own medical treatment, including the right to refuse life-sustaining interventions, free from unwarranted interference (Beauchamp & Childress, 2019).
This principle gained legal and clinical ascendancy through a series of landmark cases and the subsequent development of informed consent doctrine, advance directive legislation, and surrogate decision-making frameworks, all of which institutionalized patient self-determination as the presumptive default in clinical decision-making (Buchanan & Brock, 1989).
Medical paternalism, by contrast, refers to the restriction of a patient’s autonomy, typically justified by appeal to the patient’s own welfare, on the grounds that the patient’s judgment is compromised, incomplete, or not reflective of their authentic, stable values (Dworkin, 2020).
Contemporary bioethics scholarship distinguishes between hard paternalism, which overrides even the wishes of a fully competent patient, and soft paternalism, which intervenes only when a patient’s capacity, information, or voluntariness is genuinely in question, a distinction that proves especially significant in end-of-life contexts where capacity frequently fluctuates and is not simply present or absent (Childress & Childress, 2020).
End-of-life care presents several recurring scenarios in which the tension between autonomy and paternalism becomes acute. These include four recurring situations. The first is disagreement between physicians and patients or families over the continuation or withdrawal of life-sustaining treatment, especially where clinicians judge further treatment medically futile while patients or families wish to continue.
The second is the assessment of decision-making capacity in patients whose cognitive status is affected by terminal illness, delirium, or severe pain, raising the question of when a patient’s stated wishes can be treated as authoritative (Appelbaum, 2007).
The third is the interpretation and application of advance directives that may be ambiguous, outdated, or in apparent conflict with a patient’s currently expressed, though possibly compromised, preferences (Emanuel & Emanuel, 1998).
The fourth is the growing legal availability of medical aid in dying in an expanding number of jurisdictions, which has generated renewed debate over the proper scope of patient self-determination at the end of life and the physician’s role in facilitating or declining to facilitate such requests (Sulmasy et al., 2018).
A body of bioethics scholarship has sought to move beyond a strict binary opposition between autonomy and paternalism, proposing instead frameworks of relational autonomy, which recognize that patient decision-making is inevitably shaped by relationships, dependency, and social context, and that respecting autonomy may sometimes require supportive engagement rather than strict non-interference (Mackenzie & Stoljar, 2000).
Similarly, models of shared decision-making have been proposed as a practical and normative middle path, in which clinicians actively participate in shaping patient understanding and deliberation without imposing outcomes, potentially reconciling the values underlying both autonomy and legitimate clinical concern for patient welfare (Elwyn et al., 2016).
However, considerable disagreement persists regarding how these reconciling frameworks should be applied in the hardest cases, particularly those involving fluctuating capacity, family conflict, or requests that clinicians judge harmful, leaving the theoretical reconciliation of autonomy and paternalism incompletely resolved at the level of concrete clinical practice (Pellegrino & Thomasma, 1988).
Problem Statement and Purpose of the Study
Statement of the Problem
Despite the near-universal endorsement of patient autonomy as the guiding principle of contemporary clinical ethics, end-of-life care continues to generate cases in which clinicians, ethics committees, and courts must determine whether some degree of paternalistic constraint remains ethically justified, without a settled, generally applicable framework for resolving such cases (Jonsen et al., 2022; Sulmasy et al., 2018).
Existing bioethical literature has largely addressed autonomy and paternalism either as abstract, competing principles requiring philosophical balancing, or through case-specific analysis of individual clinical scenarios, without offering an integrated analytic framework capable of guiding the specific, recurring categories of end-of-life conflict, including capacity ambiguity, advance directive interpretation, futility disputes, and requests for medical aid in dying (Appelbaum, 2007; Emanuel & Emanuel, 1998).
This gap is problematic because clinicians, patients, and families facing these decisions in practice require more than an assertion that autonomy should generally be respected; they require a workable analytic account of when, and on what specific grounds, some constraint on stated patient wishes remains ethically defensible, and when respect for autonomy must prevail even where the patient’s choice appears imprudent to clinicians or family members (Childress & Childress, 2020).
Without such an account, clinical ethics consultation and institutional policy risk resolving individual cases inconsistently, relying on ad hoc intuition rather than a coherent, defensible bioethical framework (Pellegrino & Thomasma, 1988).
Purpose of the Study
The purpose of this bioethical analysis is to examine the philosophical foundations of autonomy and paternalism as they apply to end-of-life medical decision-making, to identify the specific clinical contexts in which these principles most sharply conflict, and to develop and evaluate a reconciling analytic framework, grounded in relational autonomy and shared decision-making theory, capable of offering more determinate ethical guidance across the recurring categories of end-of-life conflict examined.
The analysis proceeds through conceptual argument and applied case analysis rather than empirical data collection, consistent with the normative, philosophical nature of the inquiry.

Research Questions and Central Propositions
RQ1. Under what specific conditions, if any, is paternalistic constraint of a patient’s stated end-of-life treatment preferences ethically defensible?
P1. Paternalistic constraint is ethically defensible only where soft paternalism conditions obtain, namely genuine deficits in decision-making capacity, information, or voluntariness, and is not defensible merely because a patient’s competent choice appears imprudent to clinicians or family members.
RQ2. How should ambiguity or apparent conflict between a patient’s advance directive and their currently expressed, though possibly capacity-compromised, wishes be resolved?
P2. Resolution should proceed through a capacity-graded framework in which the currently expressed wishes of a patient retaining decisional capacity are given priority over a prior advance directive, while directives retain controlling authority once capacity has been genuinely lost.
RQ3. Can a relational autonomy and shared decision-making framework offer more determinate ethical guidance in end-of-life conflict than the traditional principlist balancing of autonomy against beneficence?
P3. A relational autonomy and shared decision-making framework offers more determinate guidance by reframing the clinician’s role as one of supporting authentic patient deliberation rather than simply weighing non-interference against welfare protection as competing, incommensurable values.
Significance and Theoretical Framework
Significance of the Study
This analysis carries significance for bioethical theory, clinical practice, and health policy.
Theoretically, the study contributes to the ongoing scholarly effort to move beyond a strict binary opposition between autonomy and paternalism by developing and testing a relational, capacity-graded framework against the specific recurring categories of end-of-life conflict, extending prior work on relational autonomy and shared decision-making into a more applied register (Mackenzie & Stoljar, 2000; Elwyn et al., 2016).
Practically, the analysis may directly inform clinical ethics consultation practice and institutional policy governing capacity assessment, advance directive interpretation, and requests for medical aid in dying, offering clinicians and ethics committees a more determinate, principled basis for resolving the hardest cases they encounter (Appelbaum, 2007; Sulmasy et al., 2018).
Given the continuing expansion of legal frameworks for medical aid in dying and the increasing clinical prevalence of prolonged, capacity-fluctuating terminal illness trajectories, evidence-based ethical guidance in this domain carries substantial and growing practical relevance.
More broadly, this analysis contributes to public and policy discourse regarding the proper limits of patient self-determination at the end of life, offering a framework relevant to ongoing legislative and judicial deliberation on these questions (Emanuel & Emanuel, 1998).
Theoretical Framework
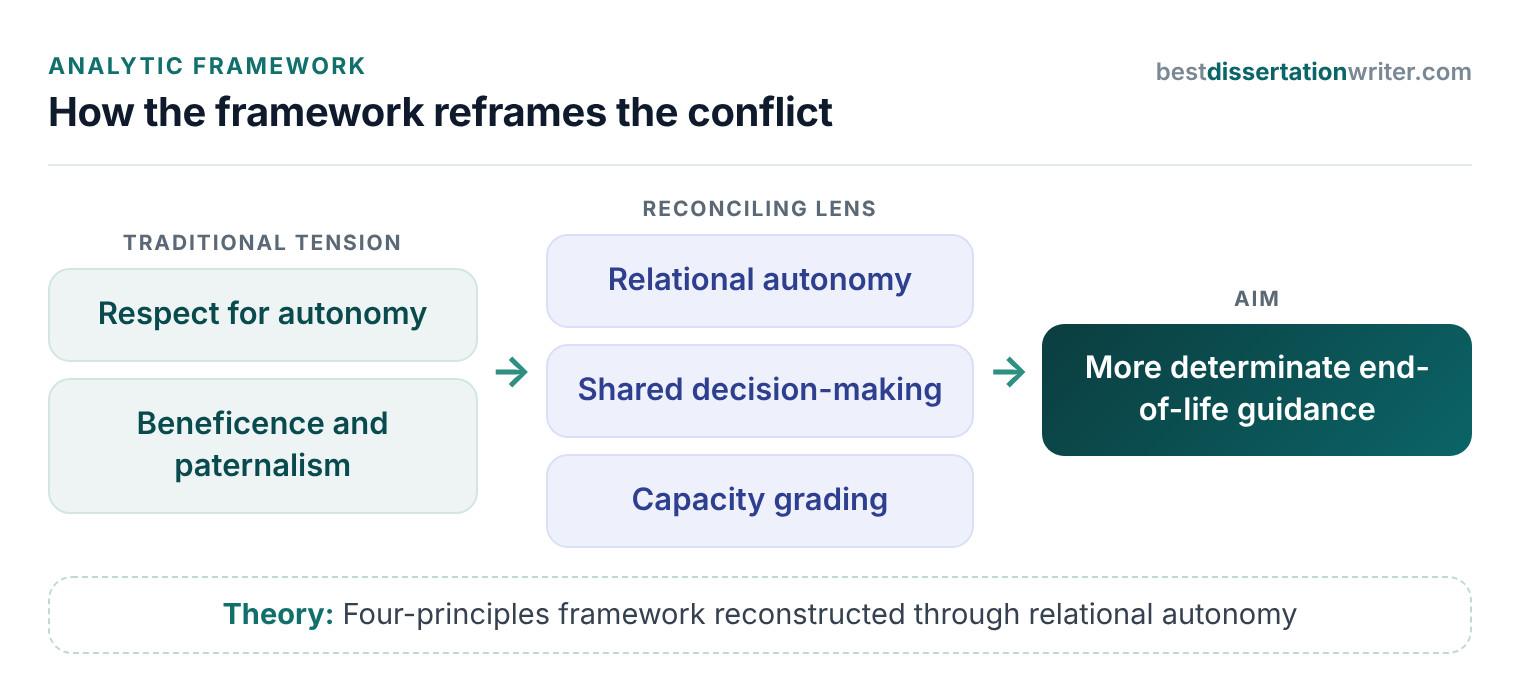
This analysis is grounded primarily in the four-principles framework of biomedical ethics, particularly the principles of respect for autonomy and beneficence, which together constitute the traditional locus of the tension between autonomy and paternalism in clinical ethics (Beauchamp & Childress, 2019).
This principlist framework provides the foundational vocabulary through which the competing claims of patient self-determination and clinician concern for welfare are traditionally articulated and weighed against one another in individual cases.
This traditional framework is paired with, and ultimately reconstructed through, relational autonomy theory, which holds that autonomous choice is never made in a social vacuum but is instead shaped, enabled, or constrained by a person’s relationships, dependencies, and social context, such that respecting autonomy may sometimes require active relational support of a patient’s deliberative capacities rather than mere non-interference (Mackenzie & Stoljar, 2000).
Integrating relational autonomy with shared decision-making theory, which reframes the clinician-patient encounter as a collaborative process of mutual deliberation rather than either unilateral clinician direction or unassisted patient choice, allows this analysis to reconstruct the tension between autonomy and paternalism as a question of how clinicians can support authentic patient self-determination under conditions of illness, dependency, and fluctuating capacity, rather than as a zero-sum trade-off between two competing principles (Elwyn et al., 2016; Pellegrino & Thomasma, 1988).
Nature of the Study, Key Terms, Assumptions and Limitations
Nature of the Study
This study employs a qualitative, conceptual bioethical analysis, integrating normative philosophical argument with applied analysis of recurring, paradigmatic categories of end-of-life clinical conflict, consistent with established methodological conventions in normative bioethics scholarship (Jonsen et al., 2022).
Rather than collecting empirical data, the analysis proceeds through systematic examination of the primary bioethics literature on autonomy, paternalism, and relational autonomy, structured argument regarding the conditions under which each principle should take priority, and applied case analysis addressing four recurring categories of end-of-life conflict: capacity ambiguity, advance directive interpretation, treatment futility disputes, and requests for medical aid in dying.
For each category, the analysis will apply the capacity-graded, relational reconciling framework developed in the theoretical framework section, testing whether the framework yields more determinate and defensible guidance than either an unqualified priority for patient autonomy or an unqualified priority for clinical judgment of patient welfare.
Representative published clinical ethics case reports and case law will be drawn upon as illustrative material to ground the conceptual analysis in recognizable clinical practice, without constituting an empirical dataset subject to statistical analysis.
Definitions of Key Terms
Autonomy: The capacity and right of a competent individual to make informed, voluntary decisions regarding their own medical treatment, free from controlling interference by others (Beauchamp & Childress, 2019).
Paternalism: The restriction of an individual’s autonomy or liberty, justified by appeal to that individual’s own welfare, good, or interests, rather than the interests of others (Dworkin, 2020).
Soft paternalism: Paternalistic intervention limited to circumstances in which a person’s decision-making capacity, information, or voluntariness is genuinely compromised, as distinguished from intervention against a fully competent, informed choice (Childress & Childress, 2020).
Relational autonomy: A conception of autonomy holding that autonomous decision-making is inevitably shaped by an individual’s relationships and social context, such that respecting autonomy may require supportive engagement rather than strict non-interference (Mackenzie & Stoljar, 2000).
Shared decision-making: A collaborative process in which clinicians and patients jointly participate in treatment decisions, combining clinical expertise with patient values and preferences (Elwyn et al., 2016).
Medical aid in dying: A legally sanctioned practice in certain jurisdictions in which a physician provides a terminally ill, decisionally capable patient with the means to end their own life at the patient’s voluntary request (Sulmasy et al., 2018).
Decision-making capacity: The functional ability of a patient to understand relevant information, appreciate the consequences of a decision, reason about treatment options, and communicate a choice (Appelbaum, 2007).
Assumptions
This analysis operates under several assumptions. It is assumed that the four-principles framework and relational autonomy theory, while originating from distinct philosophical traditions, are not fundamentally incompatible and can be productively integrated into a single reconciling analytic framework rather than treated as mutually exclusive theoretical commitments.
It is assumed that the paradigmatic clinical case categories selected for applied analysis, capacity ambiguity, advance directive interpretation, treatment futility, and medical aid in dying, adequately represent the principal contexts in which the tension between autonomy and paternalism arises in contemporary end-of-life care, though it is recognized that additional, less common conflict categories exist.
It is further assumed that published clinical ethics case material and case law provide a sufficiently accurate representation of the ethical dynamics of real clinical practice to support the applied dimension of the analysis, notwithstanding the inherent limitations of case reports as a source of clinical reality.
Scope and Delimitations
The scope of this analysis is delimited to end-of-life decision-making within adult patients in Western, primarily United States and comparable common-law jurisdictions, and does not address pediatric end-of-life ethics, which raises distinct considerations regarding surrogate authority and the child’s evolving autonomy, nor does it address end-of-life ethics within non-Western bioethical or legal traditions that may configure the relationship between autonomy and paternalism differently.
The analysis is further delimited to four specific recurring categories of end-of-life conflict, capacity ambiguity, advance directive interpretation, treatment futility disputes, and medical aid in dying, and does not extend to related but conceptually distinct domains such as resource allocation ethics or organ donation ethics.
The analysis is delimited to a conceptual, normative bioethical methodology and does not incorporate empirical survey or interview data regarding clinician or patient attitudes toward autonomy and paternalism in practice.
Limitations
Several limitations should be acknowledged. As a conceptual, normative analysis rather than an empirical study, the framework developed cannot be validated through statistical testing, and its persuasiveness rests on the strength of philosophical argument and applied case analysis rather than quantifiable evidence of improved clinical outcomes.
The reliance on published case reports and case law as illustrative material introduces a degree of selection bias, as such cases are disproportionately drawn from unusually contested or legally significant scenarios rather than the far larger number of end-of-life decisions resolved without formal ethics consultation or litigation.
The analysis’s delimitation to Western bioethical and legal traditions limits the generalizability of its reconciling framework to health systems and cultural contexts in which family-centered or physician-centered decision-making models predominate over an individualistic conception of patient autonomy (Pellegrino & Thomasma, 1988).
Finally, the rapidly evolving legal landscape surrounding medical aid in dying means that specific applied conclusions regarding this category of conflict may require revisiting as additional jurisdictions adopt or amend relevant legislation (Sulmasy et al., 2018).
Summary
This chapter introduced the background, problem, purpose, and theoretical grounding of a bioethical analysis reconciling autonomy and paternalism in end-of-life medical decision-making.
While respect for patient autonomy has become the dominant normative commitment in contemporary clinical ethics, end-of-life care continues to generate recurring categories of conflict, including capacity ambiguity, advance directive interpretation, treatment futility disputes, and requests for medical aid in dying, in which the proper scope of paternalistic constraint remains contested and insufficiently resolved by existing frameworks.
Grounded in the four-principles framework and reconstructed through relational autonomy and shared decision-making theory, this analysis proposes a capacity-graded reconciling framework intended to offer more determinate ethical guidance across these recurring categories of conflict, with implications for clinical ethics consultation, institutional policy, and health law and policy debate.
Chapter Two will present a comprehensive review of the existing bioethical and legal literature on autonomy, paternalism, and end-of-life decision-making, further situating this analysis within its scholarly context.
References
Appelbaum, P. S. (2007). Assessment of patients’ competence to consent to treatment. New England Journal of Medicine, 357(18), 1834–1840.
Beauchamp, T. L., & Childress, J. F. (2019). Principles of biomedical ethics (8th ed.). Oxford University Press.
Buchanan, A. E., & Brock, D. W. (1989). Deciding for others: The ethics of surrogate decision making. Cambridge University Press.
Childress, J. F., & Childress, M. D. (2020). What does the evolution from informed consent to shared decision making teach us about authority in health care? AMA Journal of Ethics, 22(5), E423–E429.
Dworkin, G. (2020). Paternalism. In E. N. Zalta (Ed.), The Stanford Encyclopedia of Philosophy (Winter 2020 ed.). Stanford University.
Elwyn, G., Frosch, D. L., & Kobrin, S. (2016). Implementing shared decision-making: Consider all the consequences. Implementation Science, 11, 114.
Emanuel, E. J., & Emanuel, L. L. (1998). The promise of a good death. The Lancet, 351(Suppl. 2), SII21–SII29.
Jonsen, A. R., Siegler, M., & Winslade, W. J. (2022). Clinical ethics: A practical approach to ethical decisions in clinical medicine (9th ed.). McGraw Hill.
Mackenzie, C., & Stoljar, N. (Eds.). (2000). Relational autonomy: Feminist perspectives on autonomy, agency, and the social self. Oxford University Press.
Pellegrino, E. D., & Thomasma, D. C. (1988). For the patient’s good: The restoration of beneficence in health care. Oxford University Press.
Sulmasy, D. P., Finlay, I., Fitzgerald, F., Foley, K., Payne, R., & Siegler, M. (2018). Physician-assisted suicide: Why neutrality by organized medicine is neither neutral nor appropriate. Journal of General Internal Medicine, 33(8), 1394–1399.
Why This Autonomy and Paternalism Dissertation Introduction Example Works
Philosophy and ethics dissertations follow the same chapter structure as empirical ones, but each section does a different job. This autonomy and paternalism example shows how to adapt it in four ways.
- A precise problem: The chapter does not argue that autonomy and paternalism conflict, which is well known; it argues that no settled framework resolves end-of-life cases.
- Propositions as answers: Each research question has a central proposition the analysis will defend, which gives a conceptual study the same clarity hypotheses give an empirical one.
- Method made explicit: The nature of the study explains how arguments will be tested against four recurring case types, so the method is not left vague.
- Fitting limitations: The chapter admits the framework cannot be validated statistically and that its strength depends on its arguments.
Research question: weak vs. strong
Weak
“Is paternalism ever okay in end-of-life care?”
This is informal, invites a yes-or-no answer and does not name the conditions the analysis will examine.
Strong
“Under what specific conditions, if any, is paternalistic constraint of a patient’s stated end-of-life treatment preferences ethically defensible?”
This asks for conditions, keeps “if any” open and frames a question that argument can actually answer.
How to Adapt This Structure
For a conceptual or philosophical dissertation, replace hypotheses with propositions and describe your method as a sequence of arguments and test cases. Define every contested term, because your analysis depends on those definitions.
For section-by-section guidance, see how to write a problem statement, a research question and the scope and delimitations. You can compare this chapter with the therapeutic communication in mental health nursing example, browse all dissertation introduction examples, or return to the how to write a dissertation hub.
The University of Leeds Library also keeps a collection of dissertation examples by subject.
FAQs About This Autonomy and Paternalism Dissertation Introduction
Can a dissertation be conceptual instead of empirical?
Yes. Many bioethics, philosophy and law dissertations are conceptual. Instead of collecting data, they build and test arguments against the literature and against recurring kinds of cases.
This example explains its method clearly in the nature of the study. It names the theories it will use, the four case types it will analyze, and the role of published case reports, which shows the committee that a conceptual method still has a defined, repeatable structure. Your committee will still expect a clear account of how arguments are tested, so describe that structure early in Chapter 1.
What is the difference between soft and hard paternalism?
Soft paternalism limits a person’s choice only when that choice may not be fully informed, voluntary or capacitated. Hard paternalism overrides a choice even when the person has full capacity and understanding.
The distinction is central to this example. Its first proposition argues that constraining end-of-life preferences is defensible only under soft paternalism conditions, which turns the broad tension between autonomy and paternalism into a narrower question the analysis can test. Defining both terms in your key terms section keeps the later analysis precise and consistent.
What is relational autonomy in bioethics?
Relational autonomy holds that people make choices within relationships and social contexts that can support or limit their ability to decide. Respecting autonomy may therefore mean actively supporting a patient’s deliberation, not just stepping back.
In this example, relational autonomy is paired with shared decision-making to reframe the clinician’s role. That reframing is what allows the analysis to move beyond simply balancing autonomy and paternalism toward a framework that guides specific end-of-life decisions. The theory therefore shapes both the framework and the case analysis that follows it.
Best Dissertation Writers
Want an introduction chapter like this for your topic?
Get a custom Chapter 1 written around your research problem, field and deadline.





